Care Coordination Software: Features, Benefits & How to Choose
Healthcare rarely happens in one place. A patient may move from a primary care provider to a specialist, behavioral health provider, hospital, post-acute organization, or community organization that helps with housing, food, transportation, or other social needs.
Care coordination software connects these teams and workflows so organizations can coordinate referrals, share relevant information, track patient needs, manage follow-up, and confirm services are completed.
The goal is not simply to send information from one organization to another. Effective care coordination creates visibility across the patient journey, from identifying a need to delivering and documenting the appropriate service.
This guide explains what care coordination software does, its key features and benefits, how it supports closed-loop referrals and SDOH coordination, how it differs from an EHR and case management software, examples of care coordination platforms, and how to evaluate a solution for your organization.
What Is Care Coordination Software?
Care coordination software is a digital platform that helps organize and coordinate a patient's care across multiple providers, care teams, organizations, and care settings.
The Agency for Healthcare Research and Quality (AHRQ) describes care coordination as bringing together patient care activities and information among the people involved in a patient's care so that services can be delivered more safely and effectively. Care coordination software provides the operational workflow layer that helps teams manage these activities across organizational boundaries.
Depending on the platform, care coordination software can support patient intake and assessment, referral management, closed-loop referral tracking, care plans, task management, provider and community partner coordination, secure communication, and social determinants of health (SDOH) tracking. It can also connect with electronic health records (EHRs) and health information exchanges (HIEs), while supporting appointment scheduling, patient follow-up, outcome tracking, workflow automation, analytics, and reporting.
For organizations coordinating clinical and social services, care coordination software can provide a shared workflow for referrals involving housing, food, transportation, behavioral health, financial assistance, and other health-related social needs. By bringing referral activity, communication, follow-up, and outcomes into a connected workflow, care teams can maintain better visibility across the patient journey.

Care Coordination Software vs. Care Coordination Platform
The terms care coordination software and care coordination platform are often used interchangeably. Both refer to technology that helps healthcare organizations coordinate patient care across providers, care teams, services, and organizations.
A care coordination platform may provide a broader technology environment that brings multiple coordination capabilities together, including referral management, care plans, patient outreach, provider communication, EHR integration, SDOH coordination, workflow automation, and analytics.
The distinction is generally one of scope rather than function. Care coordination software may refer to a specific application or workflow, while a care coordination platform can describe a broader set of connected capabilities.
When evaluating either option, organizations should focus less on terminology and more on whether the solution can support the complete care coordination workflow, integrate with existing healthcare systems, and provide visibility across providers and organizations.
Why Is Care Coordination Software Important in 2026?
Healthcare organizations are increasingly responsible for coordinating care across settings rather than managing isolated patient encounters.
Value-Based Care Requires Coordination
Value-based care places greater emphasis on quality, outcomes, utilization, and accountability across a patient's care journey.
CMS reported that, as of January 2026, an estimated 14.3 million Medicare beneficiaries were receiving care coordinated by Accountable Care Organizations (ACOs). The Medicare Shared Savings Program included 511 ACOs serving 12.6 million people with Traditional Medicare in 2026.
As more organizations take responsibility for quality and total cost of care, visibility across providers, referrals, and services becomes increasingly important.
Care coordination software can help teams track whether referrals are accepted, whether patients connect with the appropriate services, and whether those services are completed.
Whole-Person Care Extends Beyond Clinical Services
A patient's health can be affected by nonclinical factors such as housing instability, food insecurity, transportation barriers, financial challenges, and access to behavioral health services.
When medical and social referrals are managed separately, care teams may lack visibility into what happened after a referral.
A coordinated workflow can bring clinical and social referrals into a more connected process.
Interoperability Is Becoming More Important
Interoperability allows information to move between healthcare systems rather than forcing care teams to work across disconnected applications.
CMS's interoperability requirements include APIs designed to support information exchange and care coordination. The CMS Interoperability and Prior Authorization Final Rule includes a Provider Access API intended to facilitate care coordination and support movement toward value-based payment models.
For healthcare organizations evaluating care coordination software, interoperability should therefore be evaluated as part of the operational workflow rather than simply as a technical feature.
The important questions are:
- Can the platform integrate with existing EHRs?
- Does it support appropriate interoperability standards?
- Can relevant information move between systems?
- Can referral and outcome information be incorporated into existing workflows?
- Does the platform support appropriate permissions, consent, and security?
Care Teams Need Fewer Manual Handoffs
Referral coordinators and care managers can spend significant time checking referral status, contacting partners, following up with patients, and updating records.
Automation can reduce repetitive work by routing requests, assigning tasks, sending reminders, escalating stalled referrals, and surfacing exceptions for staff attention.
The objective is not to replace care teams. It is to give them better visibility and reduce unnecessary administrative work.
How Does Care Coordination Software Work?
Care coordination software connects the activities involved in moving a patient from an identified need to a completed service and documented outcome.
A typical workflow includes five stages.
1. Need Identification
A patient need is identified and captured in a trackable workflow. The need may be clinical, such as a specialist referral, or social, such as transportation, housing, food, financial assistance, or behavioral health support.
2. Referral and Scheduling
The patient is connected to an appropriate provider, organization, appointment, or service. The workflow may support referral routing, provider matching, scheduling, authorization, and assignment of coordination tasks.
3. Patient Outreach
The care team or automated workflow follows up with the patient to help move the referral forward.
Outreach may include:
- Appointment reminders
- Status checks
- Appointment confirmations
- Patient notifications
- Follow-up for incomplete referrals
- Escalation when additional intervention is needed
4. Visit or Service Confirmation
The referring organization receives confirmation that the patient reached the destination and that the requested service was delivered or otherwise addressed.
5. Outcome Return
Relevant status information, notes, results, or outcomes are returned to the appropriate care team. This creates visibility into what happened after the referral and helps close the coordination loop.
The key workflow is:
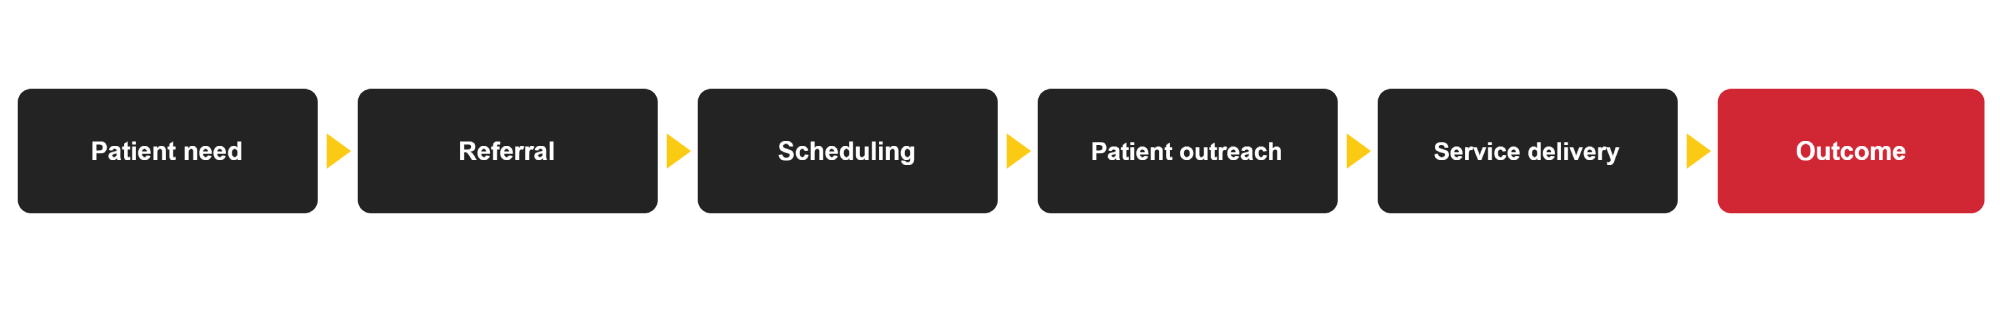
A system that only sends a referral may improve communication. A system that tracks acceptance, progress, completion, and outcomes provides a more complete care coordination workflow.
What Are the Key Features of Care Coordination Software?
Not every platform offers the same capabilities. When evaluating care coordination software, focus on the workflows your organization actually needs.
Closed-Loop Referral Management
Referral management is one of the most important capabilities to evaluate.
A closed-loop referral workflow should allow teams to:
- Create and send referrals
- Route referrals to appropriate providers or organizations
- Track referral acceptance
- Monitor referral status
- Assign follow-up tasks
- Identify stalled referrals
- Confirm completed services
- Return relevant outcomes to the referring team
Without the closing step, a referral can disappear into another organization's workflow, leaving the original care team unaware of what happened.
Shared Care Plans
Patients with complex needs may have several providers involved in their care.
Care coordination software should allow authorized teams to establish shared goals, assign responsibilities, track milestones, and monitor progress.
This is particularly important when clinical and social services need to work together.
FHIR and HL7 Interoperability
Interoperability enables information to flow between systems rather than forcing care teams to work across disconnected applications.
When evaluating a platform, ask:
- Does it support FHIR?
- Does it support HL7-based workflows?
- Which EHRs can it integrate with?
- Is the integration read-only or bidirectional?
- Can information be written back to the clinical system?
- How are patient identity matching, consent, and security handled?
AHRQ has identified poor EHR interoperability as a major obstacle to coordinating and measuring care across organizations and providers.
Workflow Automation
Automation can help care teams manage repetitive coordination activities.
Useful capabilities include:
- Automated referral routing
- Provider matching
- Task assignment
- Reminder notifications
- Escalation for stalled referrals
- Appointment follow-up
- Status updates
- Patient outreach
- Exception management
When evaluating AI-enabled capabilities, ask vendors to demonstrate what the system can actually execute within a workflow rather than focusing only on generated text.
Social Determinants of Health Tracking
Whole-person care often requires coordination between healthcare providers and community organizations.
Look for software that can manage referrals related to:
- Housing
- Food
- Transportation
- Financial assistance
- Behavioral health
- Employment
- Other health-related social needs
The important question is whether these needs can be managed within the same coordination workflow as clinical referrals.
Reporting and Analytics
Healthcare leaders need visibility into whether coordination workflows are working.
Useful metrics can include:
- Referral completion rate
- Time to service
- Referral acceptance rate
- Referral leakage
- Partner response time
- Patient outreach activity
- SDOH referral completion
- Service outcomes
- Program performance
Reporting should help teams identify where referrals stall and which workflows require improvement.
Security, Permissions, and Consent
Because care coordination involves patient information and multiple organizations, organizations should evaluate:
- Role-based access
- Consent management
- Secure communication
- Secure document sharing
- Audit trails
- Data protection controls
- Partner access controls
The platform should provide appropriate access without giving every participant unrestricted visibility into patient information.
What Are the Benefits of Care Coordination Software?
Care coordination software improves visibility across referrals, providers, and care teams. Organizations can track referrals from submission to completion, reduce referral leakage, speed up connections to services, and give authorized teams better visibility into patient and referral activity.
It also reduces administrative work through automated routing, reminders, follow-ups, and status updates. By connecting clinical referrals with social needs such as housing, food, transportation, and behavioral health, care coordination software helps organizations measure referral completion, response times, outcomes, and overall care coordination performance.
How Does Care Coordination Software Support Closed-Loop Referrals?
A closed-loop referral process provides visibility into what happens after a referral is sent.
Instead of ending when a referral is transmitted, the workflow continues through:
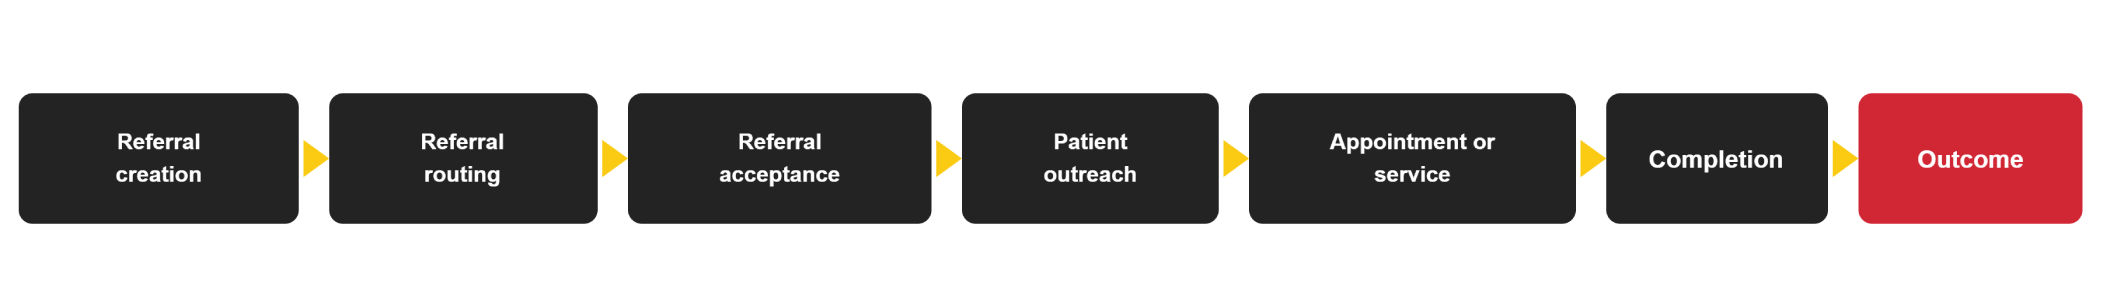
Care coordination software can help organizations monitor each stage and identify referrals that require intervention.
For example, if a referral has been sent but not accepted, the system can surface it for follow-up. If a patient has not scheduled an appointment, the care team can initiate outreach. If a service has been completed, the referring organization can receive confirmation and relevant outcome information.
This approach helps reduce the gap between sending a referral and knowing whether the patient actually received the intended service.
How Does Care Coordination Software Support SDOH?
Social determinants of health (SDOH) can influence access to healthcare and overall health outcomes. Care coordination software helps organizations include social needs within the same workflow used for clinical care coordination.
A typical SDOH workflow can move from screening and need identification to community resource matching, referral, partner acceptance, patient engagement, service completion, and outcome tracking. Common needs include housing, food, transportation, financial assistance, behavioral health, employment, childcare, and other community services. By connecting SDOH referrals with clinical workflows, care teams can maintain better visibility into both clinical and social needs without relying on disconnected processes.
Does Care Coordination Software Integrate With EHRs?
Yes. Many care coordination platforms integrate with EHRs and other healthcare systems to support the exchange of relevant patient, referral, and clinical information.
Integration capabilities vary significantly between vendors.
When evaluating EHR integration, consider:
| Integration capability | Why it matters |
|---|---|
| FHIR APIs | Supports standardized healthcare data exchange |
| HL7 | Supports healthcare messaging and interoperability workflows |
| Bidirectional integration | Allows information to move between systems |
| Patient matching | Helps connect information to the correct patient |
| Referral data exchange | Supports referral workflows across systems |
| Write-back capabilities | Can reduce duplicate documentation |
| Consent and access controls | Helps manage appropriate information sharing |
| Auditability | Provides visibility into system activity |
Integration depth is important.
A platform that only displays information from another system may still leave staff responsible for manually updating the source EHR.
A deeper integration can help connect care coordination activities to existing clinical workflows.
What Is the Difference Between Care Coordination Software, EHR, Case Management Software, and Care Management Software?
These categories overlap, but they serve different primary purposes.
| System | Primary purpose |
|---|---|
| EHR | Stores and manages the clinical record, including documentation, medications, labs, and clinical history |
| Case management software | Helps organizations manage individual cases, services, tasks, and documentation |
| Care management software | Supports structured care management programs, patient populations, care plans, and interventions |
| Care coordination software | Connects providers, organizations, referrals, services, and workflows across organizational boundaries |
An EHR remains central to clinical documentation.
Care coordination software focuses more heavily on the movement of work and information between the people and organizations responsible for a patient's care.
This distinction becomes especially important when healthcare organizations need to coordinate with external providers, specialists, post-acute organizations, or community-based organizations that may not operate inside the same EHR.
Who Uses Care Coordination Software?
Health systems, hospitals, FQHCs, ACOs, health plans, managed care organizations, and primary care providers use care coordination software to coordinate referrals, patient outreach, care transitions, and communication across multiple providers and care settings. ACOs can also use these platforms to improve visibility across participating providers and support coordinated care for defined patient populations. CMS's 2026 Shared Savings Program includes 511 ACOs, highlighting the scale of coordinated care programs in Medicare.
The software also supports behavioral health organizations, post-acute care providers, and community-based organizations. These teams can coordinate medical and social services such as behavioral health, housing, food, transportation, financial assistance, and other health-related needs through connected referral and follow-up workflows.
Best Care Coordination Software in 2026
Care coordination software varies significantly based on the workflows, care settings, and organizations each platform is designed to support.
Some platforms focus on care transitions and post-acute referrals, while others emphasize care management, chronic care programs, enterprise healthcare data, or coordination between healthcare and community organizations.
Examples in the broader care coordination market include:
| Platform | Primary focus | Common capabilities |
|---|---|---|
| WellSky | Care coordination, transitions, and post-acute workflows | Patient tracking, referrals, transitions, care management |
| athenahealth | Provider and healthcare organization workflows | EHR, practice management, care coordination, patient engagement |
| Innovaccer | Enterprise healthcare data and care management | Data integration, analytics, population health, care management |
| Netsmart | Complex, behavioral, and community-based care | Care coordination, care management, behavioral health workflows |
| CarePort | Care transitions and post-acute coordination | Discharge planning, referrals, transitions, post-acute workflows |
| ThoroughCare | Chronic care management and remote patient programs | Care management, CCM, RPM, patient engagement |
| GridSocial | Clinical and social referral coordination | Closed-loop referrals, SDOH coordination, EHR interoperability, referral tracking |
The right solution depends on the organization's care model and coordination requirements.
A hospital managing discharge and post-acute transitions may prioritize transition workflows. An FQHC, ACO, health plan, or community-focused organization may place greater importance on referral management, SDOH coordination, external partner access, and closed-loop outcomes.
Rather than selecting software based only on the number of features, organizations should evaluate how well each platform supports the complete workflow from identifying a patient need through referral, service delivery, follow-up, and documented outcome.
How Do You Choose the Right Care Coordination Software?
Before selecting a platform, use a practical buyer's checklist.
- Loop Completeness: Can the platform track the referral from the initial request through documented completion?
- Care-Setting Fit: Was the software designed for your environment, such as an FQHC, hospital, ACO, health plan, behavioral health organization, or community-based organization?
- Interoperability Depth: Does the platform integrate with your EHR and other systems using appropriate standards? Can it read and write information where required?
- Community Partner Access: Can external community organizations receive, accept, update, and close referrals without creating additional disconnected workflows?
- Automation: Does automation actually execute tasks such as routing, reminders, escalation, and follow-up?
- Analytics: Can your team measure referral completion, time to service, referral leakage, partner performance, patient outreach, and outcomes?
- Security and Permissions: Does the platform provide appropriate role-based access, consent controls, secure communication, and auditability?
- Implementation and Support: Evaluate implementation timelines, data migration, training, configuration, technical support, and service-level commitments before making a decision.
- Partner Adoption: A platform is only useful if the organizations receiving referrals can use it effectively. Evaluate how easily community partners, specialists, care teams, and other external participants can participate in the workflow.
- Live Workflow Demonstration: Do not rely only on a scripted product demo. Ask vendors to demonstrate a complete referral:
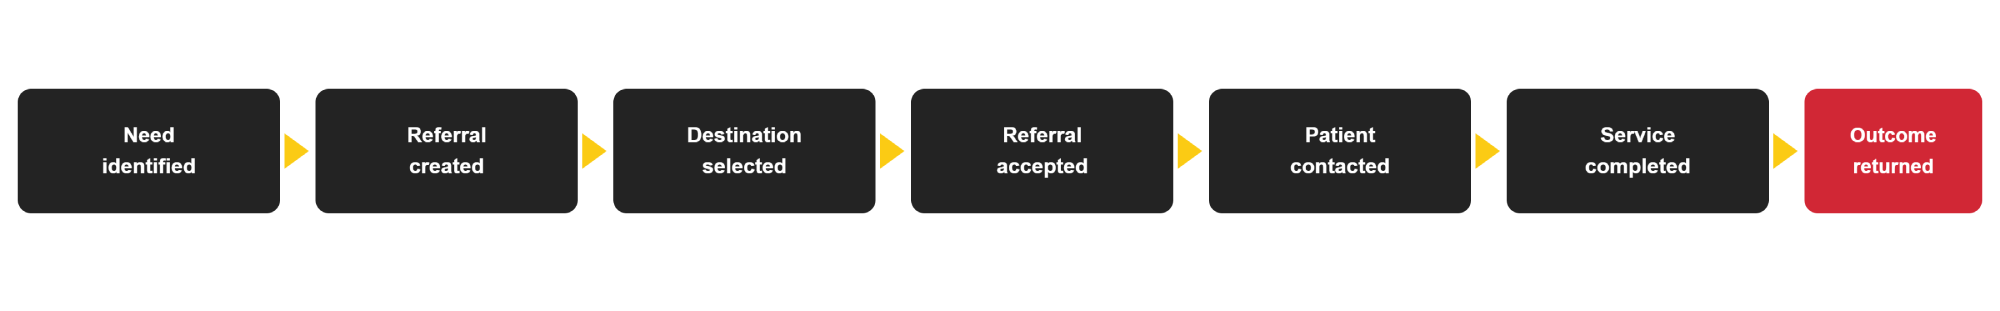
This gives your team a better understanding of whether the platform actually supports closed-loop coordination.
How Much Does Care Coordination Software Cost?
The cost of care coordination software varies based on the organization's size, number of users, patient or member volume, required capabilities, integrations, and implementation requirements.
Factors that can influence the total cost include:
- Number of users and participating organizations
- Patient, member, or referral volume
- Referral management capabilities
- Care management and care plan functionality
- EHR and interoperability integrations
- SDOH and community referral workflows
- Workflow automation requirements
- Reporting and analytics
- Implementation and configuration
- Training and ongoing support
- Custom workflows and integrations
Some organizations may require a focused referral coordination solution, while larger health systems and health plans may need broader capabilities across care management, transitions, interoperability, analytics, and external partner coordination.
When comparing vendors, organizations should evaluate the total cost of ownership rather than looking only the software subscription price.
Implementation, integrations, configuration, training, support, and ongoing administration can all affect the overall investment.
Because pricing models vary by vendor and deployment requirements, healthcare organizations should request a detailed quote based on their specific workflows, users, referral volume, and integration needs.
How Does GridSocial Support Care Coordination?
GridSocial by SocialRoots.ai is designed to connect healthcare organizations and community-based organizations through a shared care coordination and referral workflow.
The platform focuses on coordinating clinical and social referrals from intake through completion, giving care teams greater visibility into referral status and outcomes.
GridSocial supports capabilities including:
- Provider and organization matching
- AI-assisted referral matching
- Load-based referral routing
- Referral tracking
- Insurance preauthorization workflows
- Automated patient outreach
- EHR interoperability through FHIR and HL7
- SDOH tracking
- Shared case visibility
- Role-based access
- Consent management
- Secure attachments
- Superbill support
- Predictive analytics
The value lies in connecting these capabilities within a coordinated workflow rather than requiring care teams to manage referral activity across disconnected systems.
For organizations coordinating both clinical and social services, this can provide a more connected view of the patient journey and help teams identify referrals that require intervention.
If your organization is looking to integrate clinical and social referrals into a single workflow, explore GridSocial's closed-loop referral platform to see how connected care coordination can work in practice.
Ready to see it in action? Schedule a personalized GridSocial demo to explore how connected referral workflows can improve visibility, reduce manual follow-up, and support measurable outcomes.
Frequently Asked Questions
Care coordination software is a digital platform that helps healthcare organizations coordinate patient care across multiple providers, organizations, referrals, services, and care settings.
Care coordination software helps manage workflows such as referrals, patient outreach, care plans, provider communication, service coordination, follow-up, and outcome tracking.
Many care coordination platforms integrate with EHRs using interoperability technologies such as FHIR and HL7. Integration depth varies by vendor and should be evaluated based on the organization's workflow requirements.
Yes. Many platforms support SDOH workflows involving housing, food, transportation, behavioral health, financial assistance, and other community services.
Organizations can evaluate metrics such as referral completion rate, time to service, referral leakage, partner response time, staff time spent on follow-up, patient engagement, service outcomes, and program performance.
Key Takeaways
Care coordination software provides the operational layer needed to connect healthcare providers, care teams, organizations, referrals, services, and outcomes around a patient's care journey.
The strongest platforms do more than send referrals. They help organizations:
- Coordinate clinical and social services
- Track referrals through completion
- Connect care teams across organizational boundaries
- Integrate with existing healthcare systems
- Automate repetitive coordination tasks
- Measure referral performance and outcomes
- Improve visibility into the patient journey
- Support collaboration with external organizations
When evaluating a platform, focus on the complete workflow rather than the feature count.
Sources
- Agency for Healthcare Research and Quality (AHRQ) — Care Coordination
- CMS — CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F)
- CMS — 2026 CMS Interoperability Standards and Prior Authorization for Drugs Proposed Rule (CMS-0062-P)
- CMS — Application Programming Interfaces and Relevant Standards and Implementation Guides
- CMS — 2026 Medicare Accountable Care Organization Initiatives Participation Highlights